Drug Therapy

Treatment provided on a clinical trial protocol

Check the appropriate box whether the patient participated on a clinical trial during initial course of chemotherapy.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Chemotherapy administered during initial treatment course?

Check if the patient received chemotherapy administered during their initial treatment course.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Was neoadjuvant chemotherapy administered?

For GYN cases only. Indicate if the patient received neoadjuvant chemotherapy. If the patient received chemotherapy but did not have surgery, answer “yes” to this question.

Additional Information
 

For gynecologic oncology cases in which the patient receives chemotherapy but there is no surgery performed, abstractors will need to choose BOTH “chemotherapy administered” and “neoadjuvant chemotherapy administered” in order for the chemotherapy drug information to populate. This will also populate the additional “was patient given anticoagulation medications concurrently with neoadjuvant chemotherapy” as well as the pre chemotherapy lab results data items.

Looking for help with something we haven’t covered here? Send us a message!

Route of Neoadjuvant chemotherapy

Check the box in which the route of neoadjuvant chemotherapy was given. Check all that apply.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Was the patient given anticoagulation medications concurrently with neoadjuvant chemotherapy?

For GYN cases only. Indicate if the patient was prescribed any of the anticoagulation medications listed in the help text within 30 days of starting neoadjuvant chemotherapy. Anticoagulation medications include LMWH/low molecular weight heparin,Warfarin/Coumadin, Apixaban/Eliquis, Rivaroxaban/Xarelto, Fondaparinux/Arixtra,Dabigatran/Pradaxa, and Edoxaban/Savaysa. “Concurrently” is defined as +/-30 days from neoadjuvant therapy start date

Additional Information
 
  • If a patient is already on long-term anticoagulation for another reason prior to the start of neoadjuvant chemotherapy, indicate yes for anticoagulation prescribed with neoadjuvant chemotherapy and indicate the date the patient was started on anticoagulation therapy.
  • If you can only locate the month and year the patient began anticoagulation therapy, indicate the first day of the month and year known.  For example, if the patient was prescribed Apixaban on 5/2016, enter 05/01/2016
  • If you can not locate any information about the date the patient was prescribed anticoagulation therapy, enter the same date as the date of the start of neoadjuvant chemotherapy.
  • If you are unable to find the term “contraindicated” documented in the provider notes, mark “no”
  • If you are unable to find the reason VTE Prophylaxis is contraindicated, leave the (specify Reason, if given) free text field blank.
  • Do not spend more than 5 minutes searching for the reason for contraindication

Looking for help with something we haven’t covered here? Send us a message!

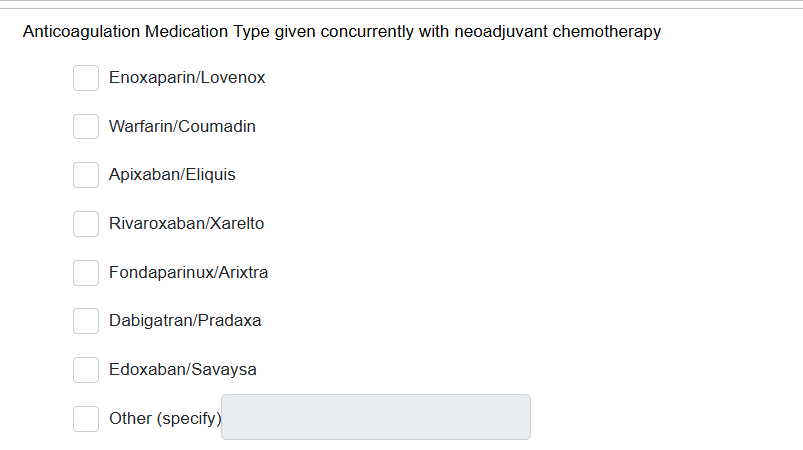
Anticoagulation Medication Type

If you answer "Yes" to the patient given anticoagulation medications concurrently with neoadjuvant chemotherapy, then indicate what anticoagulation medications were given to the patient within 30 days of starting.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Was adjuvant chemotherapy administered?

For GYN cases only. Indicate if the patient received adjuvant chemotherapy after their surgery. If the patient did not have surgery, answer “No” to this question.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Route of Adjuvant Chemotherapy

Check the box in which the route of adjuvant chemotherapy was given. Check all that apply.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Neoadjuvant chemotherapy start date

If you answered yes to patient received neoadjuvant, enter the start date for any/all neoadjuvant chemotherapy routes selected.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Adjuvant chemotherapy start date

If you answered yes to patient received adjuvant, enter the start date for any/all adjuvant chemotherapy routes selected.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Start Date IV chemotherapy during Cycle 1 of Initial Anticancer therapy Treatment

Provide the start date for the IV chemotherapy during Cycle 1 of initial anticancer therapy treatment. If patient received both neoadjuvant & adjuvant chemotherapy, use start date of neoadjuvant chemotherapy.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Did the regimen contain Cisplatin?

Indicate whether or not the patient received Cisplatin at any point during the initial regimen, not just Cycle 1.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Did the regimen contain Carboplatin?

Indicate whether or not the patient received Carboplatin at any point during the initial regimen, not just Cycle 1.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

What is the AUC?

If the patient received Carboplatin, enter the Carboplatin AUC.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Did the regimen contain Taxane?

Indicate whether or not the patient received Taxane at any point during the initial regimen, not just Cycle 1.

Additional Information
 

Taxanes

  • Generic = paclitaxel, docetaxel
  • Brand = Taxol, Abraxane, Taxotere

Looking for help with something we haven’t covered here? Send us a message!

Did the regimen contain Doxorubicin & Cyclophosphamide?

Indicate whether or not the patient received Doxorubicin & Cyclophosphamide at any point during the initial regimen, not just Cycle 1.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Did the patient receive FOLFIRINOX (irinotecan, oxaliplatin, 5-FU, and leucovorin)?

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Emetic Risk for Chemotherapy received

Indicate the emetic risk of the patients chemotherapy regimen given for Cycle 1, day 1 of initial IV chemotherapy. Review the chemotherapy flowsheet. Respond based on the highest Emetic risk agent administered, if more than one chemotherapy drug administered.

Additional Information
 

Refer to MOQC’s Emetic Risk vs immunotherapy drug list. MOQCs Emetic Risk vs Immunotherapy Document

NOTE: This document is updated periodically.

Looking for help with something we haven’t covered here? Send us a message!

Is this patient participating in an antiemetic clinical trial?

Indicate if the patient is on an antiemetic clinical trial.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

NK1 Receptor Antagonist Administered

If more than one high emetic risk drug was administered, reference the first administration when checking for aprepitant (Emend) OR netupitant (AKYNZEO®) or rolapitant.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Start Date NK1 Receptor Antagonist Administered

Provide start date for the NK1 Antagonist Administered for Cycle 1 IV Chemotherapy.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Was Olanzapine prescribed

During Cycle 1 of initial IV chemotherapy, indicate if olanzapine was prescribed.

Additional Information
 

Common brand names for olanzapine: Zyprexa Relprevv, Zyprexa Zydis, Zyprexa

Looking for help with something we haven’t covered here? Send us a message!

Documented intent of chemotherapy within 60 days prior or 14 days after anticancer therapy administration

This question will only populate for ovarian, fallopian tube, and primary peritoneal cancers and no longer populates for medical oncology. Indicate whether there is documentation/acknowledgement of intent for the initial treatment course, by a practitioner in the practice. • Palliation may be to prolong life (without goal of cure) or to control symptoms.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

PARP-Inhibitor prescribed (GYN ONC Cohort only)

Documentation may be found under the oncology treatment or medication section in the EMR, as they are usually given as tablets or capsules. Enter whether the PARP-Inhibitor was prescribed (yes or no), which one was prescribed (from the 3 choices) and the date that the PARP-Inhibitor was prescribed. If the prescribed date cannot be determined, choose the unknown box for the date.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

PARP-Inhibitor type (GYN ONC Cohort only)

Choose between Olaparib, Rucaparib, Niraparib or unknown.

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!

Date PARP-Inhibitor prescribed (GYN ONC Cohort Only)

Additional Information
 

Looking for help with something we haven’t covered here? Send us a message!
